
4.1 Complement #
The study of Complement provides fundamental principles governing cellular architecture, molecular interactions, and physiological regulation.
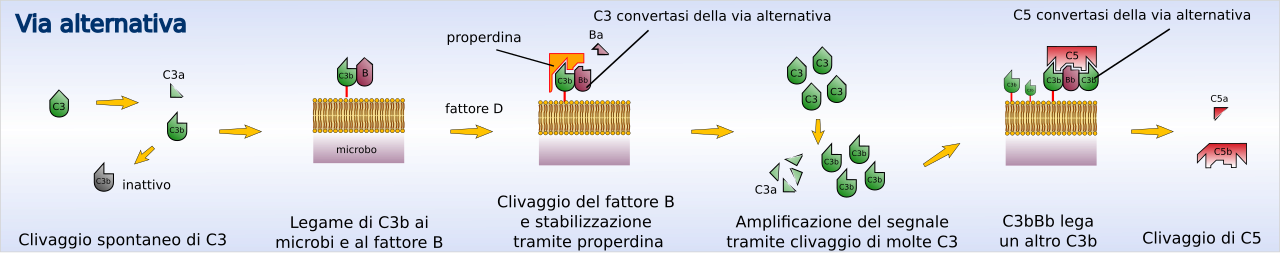
Complement Alternative
4.1.1 Three routes, one convertase #
Complement is a proteolytic cascade in blood and tissue fluid. Three routes converge on a C3 convertase, and C3 cleavage is the amplification point. The classical pathway starts when C1q binds Fc on antibody already bound to antigen. One surface-bound IgM can engage several of C1q’s six heads; IgG must be clustered, and in humans IgG1 and IgG3 do this well while IgG4 essentially does not. C1s cleaves C4 and C2, and C4b2a, in the classical fragment names, is the C3 convertase. The lectin pathway builds the same C4b2a without antibody: mannose-binding lectin or a ficolin binds microbial carbohydrate, and the associated MASPs cleave C4 and C2. The alternative pathway needs neither. Slow hydrolysis of C3 (tickover) lets factor B bind and factor D cut it, producing a little C3b. Surface C3b binds more factor B, and C3bBb, stabilised by properdin, is the alternative C3 convertase. Deposition amplifies wherever regulators are missing.
| Route | What starts it | Proteases | C3 convertase |
|---|---|---|---|
| Classical | Fc of bound IgM or clustered IgG | C1r, C1s | C4b2a |
| Lectin | Microbial carbohydrate | MASPs | C4b2a |
| Alternative | C3 tickover on an unprotected surface | Factor D | C3bBb |
4.1.2 Opsonisation, anaphylatoxins, and the membrane-attack complex #
C3b binds covalently to the nearest surface and is the main opsonin. Phagocytes take it up through CR1, and take up the inactivated fragment iC3b through CR3 (Mac-1, CD11b/CD18). A convertase that has gained an extra C3b cleaves C5. C3a and C5a are anaphylatoxins: they increase vascular permeability and act on mast cells, and C5a also attracts neutrophils. C5b recruits C6, C7, C8, and many copies of C9. Polymerised C9 is the pore of the membrane-attack complex, C5b–C9. It lyses thin-walled Gram-negative bacteria. Thick walls and capsules are controlled by opsonisation instead. C3d bound to antigen is also read by CR2 (CD21) on B cells, which lowers the threshold for B-cell activation.

Tcr Complex
4.1.3 How host cells are spared, and what failure looks like #
Host surfaces are spared by regulators. Factor H binds sialic-acid-rich surfaces and, with factor I, cleaves C3b so that it cannot form a convertase. CD55 dismantles convertases, CD46 helps factor I, and CD59 stops C9 from finishing the pore. Loss of C3 removes every route’s opsonin and causes severe pyogenic infection together with poor clearance of immune complexes. Loss of C1q more often looks like lupus, because apoptotic debris is not cleared. Loss of a terminal component (C5–C8) or of properdin is narrow: recurrent invasive Neisseria, especially meningococcus, because opsonisation still works and the pore is what matters for that organism in blood. C9 deficiency is often milder, since C5b–C8 retains some lytic activity.
4.2 Phagocyte killing #
4.2.1 Uptake and the respiratory burst #
Phagocytes bind particles through Fcγ receptors, complement receptors, or pattern receptors, close a phagosome, and fuse it with lysosomes that supply acid and proteases. Neutrophils also deliver myeloperoxidase. NADPH oxidase assembles in the phagosome membrane. Its catalytic subunit is gp91phox (NOX2), with p22phox and the cytosolic partners p47phox, p67phox, p40phox, and Rac. It transfers electrons from NADPH to oxygen, making superoxide inside the vacuole. Superoxide becomes hydrogen peroxide, and myeloperoxidase converts that, with chloride, into hypochlorite. This oxygen consumption is the respiratory burst, separate from mitochondrial respiration. IFN-γ from Th1 or NK cells is the signal that makes a macrophage kill a microbe it might otherwise shelter.
4.2.2 Chronic granulomatous disease #
Chronic granulomatous disease is loss of an oxidase subunit. The commonest form is X-linked, in gp91phox (CYBB). Phagocytes ingest and degranulate and fail to make superoxide, so organisms the burst would have killed persist and are walled off by macrophages and T cells as granulomas. A tuberculous granuloma, which Microbiology describes, is a resistant microbe facing an oxidase that still works. The histology can look alike; the defect does not.
4.3 Inflammation and NK cells #
4.3.1 Local inflammation #
TNF, IL-1, and IL-6 from macrophages and dendritic cells dilate arterioles (redness and heat), open post-capillary venules so that plasma, antibody, and complement leak (swelling), and, with bradykinin and prostaglandins, cause pain. Leucocytes then leave the blood in order. Selectins mediate rolling on sialyl-Lewis X. CXCL8 displayed on endothelium activates neutrophil integrins, and LFA-1 and Mac-1 arrest the cell on ICAM-1. The cell crosses at junctions that include PECAM-1. In leucocyte-adhesion deficiency type I, CD18 is missing, β2-integrin arrest fails, neutrophils remain in the blood, and pus does not form.
4.3.2 Fever and the acute-phase response #
IL-1, IL-6, and TNF induce prostaglandin E2 in the hypothalamus and raise the thermal set point, so fever is a defended higher temperature. The same cytokines in large amounts cause widespread leak, hypotension, and disordered coagulation. IL-6 also resets the liver: C-reactive protein, serum amyloid A, fibrinogen, mannose-binding lectin, and several complement proteins rise, and albumin falls. C-reactive protein binds phosphocholine and can start the classical pathway without antibody. Fibrinogen speeds red-cell sedimentation, which is why the erythrocyte sedimentation rate rises. These proteins report that IL-6 has reached the liver; they do not name a single disease.
4.3.3 NK cells and missing self #
NK cells kill without gene rearrangement and without priming in a node. Kärre’s missing-self rule is a balance. Inhibitory receptors read MHC class I: killer immunoglobulin-like receptors recognise groups of HLA-B and HLA-C, and NKG2A/CD94 recognises HLA-E, which displays peptides from the leader sequences of classical class I. Activating receptors, notably NKG2D, bind stress ligands such as MICA, MICB, and the ULBPs. A cell that has lost class I to hide from CD8 cells loses the inhibitory signal and, if activating ligands are present, is killed with perforin, granzymes, and Fas ligand. CD16 (FcγRIII) lets the same cell kill IgG-coated targets, with the antibody supplying the specificity. Type I interferon and IL-12 increase NK activity and early IFN-γ, which activates macrophages before antigen-specific T cells are numerous.
4.4 Key terms, summary, and self-check #
Key terms. C4b2a; C3bBb; C3b; anaphylatoxin; membrane-attack complex; factor H; CD59; NADPH oxidase; chronic granulomatous disease; selectin; integrin; acute-phase response; missing self; KIR; CD16.
Summary. Classical and lectin pathways build C4b2a; the alternative pathway builds C3bBb where regulators are missing. C3b opsonises, C3a and C5a inflame, and C5b–C9 lyses susceptible bacteria, which is why terminal-complement deficiency presents as invasive neisserial disease. Phagocytes kill with the NADPH oxidase; without it, chronic granulomatous disease follows. TNF, IL-1, and IL-6 drive local inflammation, fever, and the acute phase. NK cells kill targets that have lost MHC class I or that are coated with IgG.
Self-check.
1. Which two pathways share C4b2a, and what is the alternative-pathway C3 convertase?
2. What are the functions of C3b, C5a, and C5b–C9?
3. Why does terminal-complement deficiency predispose to Neisseria rather than to every bacterium?
4. Which enzyme complex is missing in chronic granulomatous disease, and what does the cell then fail to make?
5. What does an NK cell read as missing self, and which receptors do that reading?
—
—
—